What Is the Anion Gap?
The anion gap is a derived value that helps clinicians interpret a person’s electrolyte status and acid-base status. It comes from a standard blood test that checks key electrolytes, especially sodium, chloride, and bicarbonate. Although many charged particles exist in the body, not all of them are directly measured on standard lab panels. The anion gap reflects the amount of unmeasured anions in the blood.
In simple terms, the anion gap is a useful hint. It is not a diagnosis by itself, but it can point toward an acid-base disorder, especially when there is low bicarbonate and signs of metabolic acidosis. Clinicians use it as part of lab interpretation on a serum chemistry panel or blood chemistry panel to understand whether acid is accumulating in the body.
The basic idea behind the anion gap formula is that the measured positive charge, mainly sodium, should roughly match the measured negative charges, mainly chloride and bicarbonate. When that balance shifts, the calculated value varies. This is why the anion gap can reveal acid accumulation even when the problem is not obvious from symptoms alone.
Because it reflects chemistry rather than a single disease, the anion gap has clinical significance across many settings. It can help explain everything from mild electrolyte imbalance to serious illness. That is why understanding the number matters, especially when a lab report shows something outside the expected range.
How an Anion Gap Calculator Functions
An Anion Gap Calculator serves as a simple utility that relies on lab values from a standard blood test to calculate the anion gap. Most calculators use sodium, chloride, and bicarbonate, although some formulas may also factor in potassium. The result is a calculated value that aids identify whether the balance of measured ions points to extra acids in the bloodstream.
The calculation is usually based on sodium minus the sum of chloride and bicarbonate. This creates a practical estimate of the gap between measured cations and measured anions. When that gap is greater than expected, it may suggest the presence of additional unmeasured acids, toxins, or other substances affecting the body’s chemistry.
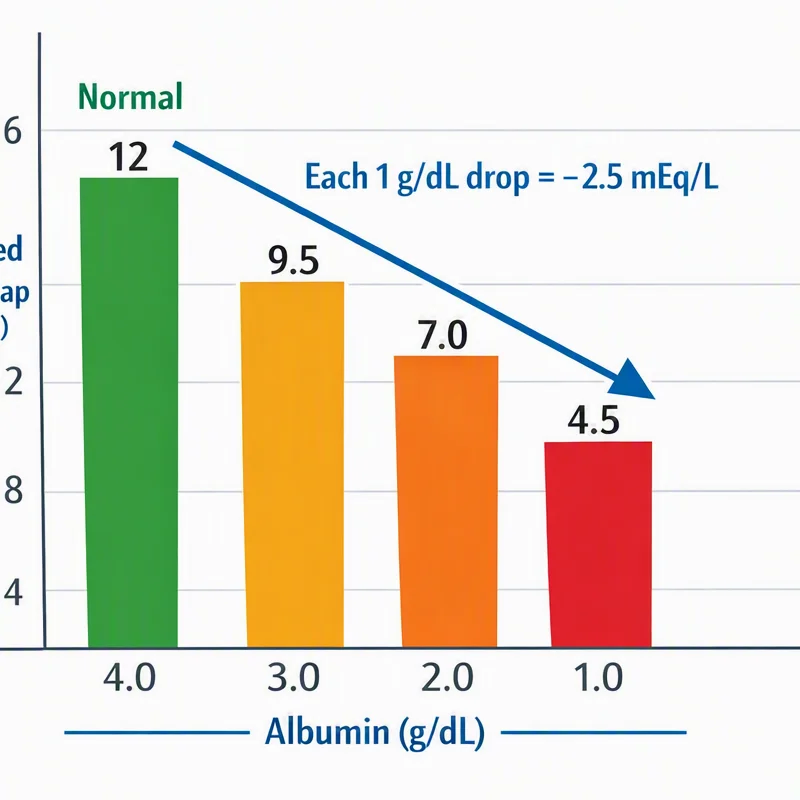
One important limitation is that the raw number can be affected by albumin, the main negatively charged protein in the blood. Low albumin can make the anion gap appear reduced than it truly is. For that reason, clinicians may use albumin correction when interpreting the result. Correcting for albumin helps prevent missing an important acid-base problem.
The calculator is most useful when seen as part of a larger picture. It does not replace albumin and anion gap interpretation medical judgment or a full diagnostic workup. Instead, it supports lab interpretation by showing whether the chemistry pattern fits with conditions such as metabolic acidemia or another form of acid-base imbalance. In other words, the calculator helps transform raw numbers into actionable information.
Because the anion gap depends on a serum chemistry panel, the quality of the input matters. If sodium, chloride, or bicarbonate values are inaccurate or incomplete, the result may be misleading. A good calculator simply applies the anion gap formula to the available lab values and then reminds the user that the number must be interpreted in context.
What Is Considered a High Anion Gap?
A standard range for the anion gap can vary slightly from one laboratory to another because each lab may use different procedures and reporting standards. That is why you should always check a result with the lab’s listed reference range rather than using a single universal cutoff. In many cases, the normal range is fairly narrow, but the exact numbers depend on the lab.
A high anion gap means the calculated number is above the expected range. This often signals that extra acids are present in the blood, which can lead to metabolic acidosis. The high value is not the disease itself; it is a marker that the body’s chemical balance has shifted in a way that warrants investigation.
Doctors often consider a high anion gap as evidence of an increased burden of unmeasured acids or other charged substances. That is why it is especially important in patients with symptoms, abnormal vital signs, or a known medical problem. A high result can help focus the possible causes of an acid-base disorder and shape next steps in care.
It is also important to understand that a number slightly outside the expected range may not be dangerous on its own. The meaning depends on the full clinical picture, including the patient’s history, symptoms, kidney function, and other lab results. A high anion gap is a clue, not a final answer.
When clinicians see a high value, they usually ask whether it fits with metabolic acidosis caused by acid buildup, toxin exposure, or impaired clearance. The pattern matters as much as the number. That is why the result should always be interpreted alongside other findings rather than in isolation.
Typical Reasons of a High Anion Gap
Various health issues can lead to a high anion gap, and many of them involve acid buildup. A common one of the main is lactic acidosis, which happens when lactate rises more rapidly than the body can eliminate it. This can occur with poor oxygen availability, serious illness, shock, or intense stress on the body.
A second common cause is ketoacidosis, in which the body breaks down fat for fuel and produces acidic ketones. A well-known example is diabetic ketoacidosis, a severe complication of diabetes that can arise when insulin is too low. Ketoacidosis can also occur with extended fasting, heavy alcohol use, or additional metabolic stressors.
Kidney failure can also lead to a high anion gap because the kidneys are less able to remove acids from the body. As kidney function declines, acids collect, and the blood chemistry alters. This is one reason why the anion gap is useful in evaluating patients with renal disease or unexplained metabolic changes.
Toxins are another important category. Certain poisons or drug exposures can create a dangerous acid-base pattern. Examples include ethylene glycol, which is found in some antifreeze products, and salicylates, which can be toxic in high doses. These are examples of toxic ingestion that may cause a high anion gap and require urgent attention.
Other conditions may also contribute, but these are among the most important clinically most important clinically. In each case, the anion gap reflects the same underlying general issue: extra unmeasured acids or other negatively charged substances are affecting the blood. The cause may be temporary or severe, but it should be identified NAGMA causes quickly so treatment can begin.
Symptoms and Alerts
A raised anion gap may be found on a lab result ahead of symptoms are obvious, but many people can develop warning signs. Common symptoms include shortness of breath, confusion, nausea, and vomiting. These symptoms can reflect the body trying to compensate for an acid-base problem or the effects of the underlying illness itself.
Shortness of breath can happen when the body tries to expel carbon dioxide to partially balance the acid load. Confusion may appear when the brain is impacted by severe metabolic changes, infection, toxin exposure, or poor organ function. Nausea and vomiting are also common in many conditions that cause acid buildup.
Warning signs become more concerning if they worsen quickly or occur with weakness, dehydration, chest discomfort, severe fatigue, or reduced alertness. In those situations, the high anion gap may reflect a major medical problem rather than a mild imbalance. The combination of symptoms and lab findings is what drives urgency.
Because symptoms can intersect across many disorders, they are not specific to one cause. Still, when symptoms match a high anion gap and low bicarbonate pattern, clinicians think seriously about the possibility of an emergency. Early recognition can make a major difference in outcome.
How Physicians Diagnose the Source
When a increased anion gap is found, the subsequent step is usually a careful workup for diagnosis to identify the causative condition. Clinicians often begin with a metabolic panel, which supplies the key electrolyte values needed to calculate the gap and assess kidney function and bicarbonate levels. That offers a rapid overview of the body’s chemistry.
An arterial blood gas may be ordered to assess the extent of the acid-base disturbance. It shows blood pH, carbon dioxide, and oxygen-related values, helping determine whether the patient has metabolic acidosis and whether the body is compensating appropriately. This adds important context beyond the basic lab numbers.
Serum lactate is often checked when lactic acidosis is suspected. An high lactate level supports the idea that acid buildup is being driven by poor oxygen delivery, tissue stress, or another serious underlying condition. Within the appropriate clinical setting, this can be an important clue.
Urine analysis is also useful, especially if ketoacidosis or kidney problems are suspected. It can detect ketones, glucose, or other signs that help refine the diagnosis. In patients with diabetes, a urine test may support the diagnosis of diabetic ketoacidosis, while other findings may point to infection or kidney involvement.
Clinicians may also review medications, exposure history, and other laboratory results to look for toxin exposure, kidney dysfunction, or another source of acid-base disturbance. The goal is to relate the calculated value to the underlying condition, because treatment depends on the cause.
Treatment and When to Ask for Help
Treatment for a high anion gap focuses on the root cause. No one treatment fixes the number itself. Instead of that, clinicians manage the problem creating the acid buildup, whether that is infection, poor circulation, diabetes, kidney failure, or toxin exposure. Once the cause is controlled, the anion gap often goes down.
Intravenous fluids are commonly used when dehydration, shock, or poor circulation is driving the imbalance. Fluids can improve perfusion, support kidney function, and help the body clear acids more effectively. In some cases, additional treatments are needed at the same time.
Insulin is a key treatment in diabetic ketoacidosis because it stops ketone production and helps the body resume normal glucose use. If the cause is a toxin, treatment may involve antidotes, specific elimination methods, or intensive supportive care. If kidney failure is severe, dialysis may be necessary under medical supervision.
You should seek emergency care if a high anion gap is paired with severe symptoms such as confusion, difficulty breathing, persistent vomiting, chest pain, extreme weakness, or reduced responsiveness. These may be signs of a dangerous acid-base problem or another urgent medical issue. A high value on its own may not always be an emergency, but a high value with symptoms should be taken seriously.
Even when symptoms are mild, timely evaluation matters if the lab pattern suggests significant metabolic acidosis. The anion gap can provide an early warning that something serious is happening before the situation worsens. Quick evaluation allows doctors to identify the cause, start treatment, and reduce the risk of complications.
FAQ
What is a high anion gap?
A high anion gap means the calculated value is above the lab’s expected range, suggesting there are extra unmeasured acids or other charged substances in the blood. It often points to metabolic acidosis and should be interpreted with the full clinical picture.
What’s the normal anion gap range?
The normal range varies by laboratory because reference methods are not identical. Be sure to compare your result with the lab’s listed reference range rather than using a single universal number. A result outside this range may still need clinical context to understand its meaning.
Can dehydration cause a high anion gap?
Dehydration by itself does not always cause a high anion gap, but it can contribute indirectly by worsening kidney function, decreasing circulation, or increasing the risk of lactic acidosis or ketoacidosis. The underlying cause matters more than dehydration alone.
Is an elevated anion gap necessarily an emergency?
No, not always. Some mild elevations may not be urgent, especially if there are no symptoms and the cause is already known. But a high anion gap with shortness of breath, confusion, nausea, vomiting, or other severe symptoms may require emergency care.
How is an anion gap corrected for low albumin?
Because albumin is a negatively charged protein, low albumin can make the anion gap appear falsely low. Clinicians apply an albumin correction to adjust the calculated value and better estimate the true gap. This helps improve lab interpretation and reduces the chance of missing a clinically important acid-base disorder.