An anion gap calculator is a useful tool for interpreting lab results that helps analyze electrolyte patterns in a serum chemistry panel. It is not a diagnosis by itself, but it can offer a important diagnostic clue when reviewing blood chemistry results and evaluating acid-base balance. By comparing the measured serum sodium, serum chloride, and serum bicarbonate, the calculator estimates the anion gap, which can help identify an electrolyte imbalance or a broader acid-base disorder.
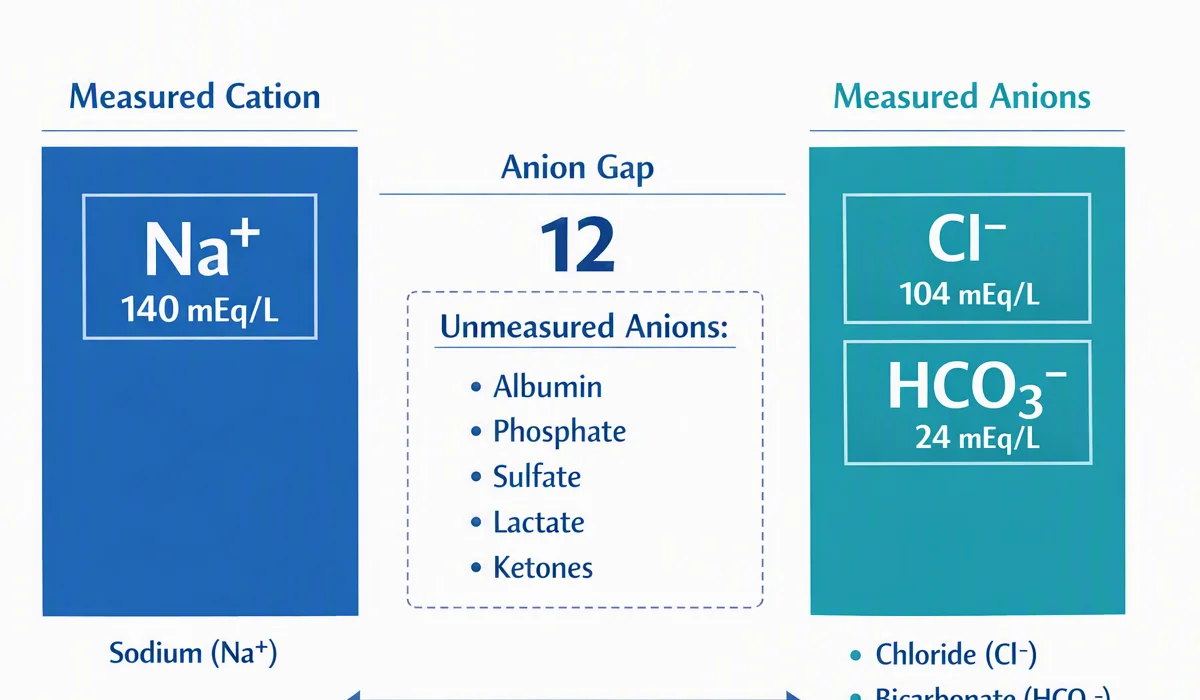
Understanding the anion gap is especially useful when reviewing an electrolyte panel, a basic metabolic panel, or a comprehensive metabolic panel. These tests are commonly used in medical screening, patient evaluation, and diagnostic workup. The result can support clinical decision support, but it should always be interpreted alongside symptoms, history, and other supportive findings.
What exactly the Anion Gap Shows
The anion gap reflects the balance between the main positive and negatively charged particles in the blood, using routine serum electrolytes. In other words, it compares the amount of sodium with the combined amount of chloride and bicarbonate. Since routine lab tests do not directly detect every charged particle in the blood, the anion gap estimates the amount of unmeasured anions.
This makes anion gap a useful marker in lab interpretation. If the gap is elevated, it may suggest that acids or other unmeasured substances are building up in the body. If the gap is reduced, it may suggest changes in albumin, lab variation, or more rarely another underlying issue. In clinical practice, this result often functions as a diagnostic clue rather than a final answer.
The anion gap is most often checked when a provider is looking for a metabolic disturbance, especially if there is concern for metabolic acidosis. It can help focus the differential diagnosis and guide a more targeted evaluation.
Anion Gap Formula and Calculation
The standard anion gap formula is:
Anion gap = plasma sodium - (plasma chloride + serum bicarbonate)
In general use, this indicates the calculator takes the plasma sodium, deducts the combined amount of plasma chloride and serum bicarbonate, and produces an anion gap value. Some calculators may also allow slightly different formulas depending on whether potassium is included, but the standard version does not include potassium.
This calculation is often done from lab values in a basic metabolic panel or comprehensive metabolic panel. Because the formula depends on the blood chemistry values reported by the laboratory, even small differences in testing methods or reference standards can affect the result. That is why checking the particular reference range used by the lab matters.
The anion gap calculation is a valuable form of clinical decision support because it helps identify patterns that might not be obvious from the individual numbers alone. For example, a low bicarbonate with a normal or elevated gap suggests different possibilities than a low bicarbonate with a normal gap.
How to Interpret a Typical, Increased, or Decreased Anion Gap
A typical anion gap usually means the lab electrolytes are in a range consistent with ordinary pH balance. However, a normal result does not always exclude disease. It simply suggests the result does not strongly point to excess unmeasured acids.
A elevated anion gap metabolic acidosis is a major finding because it often shows that acids are building up in the body. This can happen when the body generates too much acid, cannot clear acid effectively, or is exposed to a substance that generates acid. A high gap is often one of the most important patterns in an acid-base disorder and can be a key diagnostic clue during patient evaluation.
A decreased anion gap is less common. It may be caused by laboratory variation, changes in proteins, or certain medical conditions. A major factor to consider is albumin, since this protein carries negative charge in the blood and affects the gap. When albumin is low, the anion gap may appear reduced than expected even if the overall clinical picture indicates otherwise.
Understanding the result requires context. The same anion gap value can have different meaning depending on the presence of symptoms, kidney function, medication use, and other lab abnormalities. That is why the result should be viewed as part of an overall interpretation guide rather than as a standalone diagnosis.
Common Sources of an Abnormal Anion Gap
Various conditions can result in an irregular anion gap. Some are emergent and demand rapid review, while others are more chronic or related to other lab results.
- Lactic acidosis can raise the gap when lactic acid accumulates, often during poor tissue oxygenation, severe illness, or shock. Ketoacidosis, including diabetic ketoacidosis or starvation-related ketosis, can also create a high gap because ketones are unmeasured anions. Renal failure may impair the body’s ability to eliminate acids, leading to accumulation of unmeasured acids and a high gap. Toxic alcohol ingestion is another important source of a high gap and can be associated with serious metabolic derangement.
These causes are part of the differential diagnosis when a provider notes an abnormal lab result. The pattern does not prove a specific condition on its own, but it can help guide the diagnostic workup. For example, high-gap acidosis may prompt screening for ketones, lactate, kidney function, or toxin exposure.
Not all acid-base disorders raise the gap. In normal anion gap metabolic acidosis, bicarbonate is lost or reduced, but the gap persists about the same because chloride often rises to compensate. This is sometimes described as a chloride shift, where chloride replaces lost bicarbonate to preserve electrical balance.
That distinction is medically important. A normal gap and a high gap point to different mechanisms, so the calculator helps structure the interpretation of blood chemistry results.
Recalculating the Anion Gap for Albumin
Hypoalbuminemia, meaning low albumin, can make the measured anion gap appear lower than it truly is. Since albumin is one of the primary negatively charged proteins in the blood, it affects the balance of charged particles and the final gap value. This is why albumin correction is often recommended when interpreting results in hospitalized or ill patients.
A corrected anion gap is calculated by adjusting the measured value upward when albumin is low. The exact correction method can vary by institution, but the basic idea is the same: if albumin is reduced, the anion gap should be read with caution because the raw number may underestimate the presence of unmeasured acids.
The reason this matters comes down to protein binding and charge balance. Albumin normally contributes negative charge, so when levels fall, the body may seem to have fewer unmeasured anions than it actually does. Correcting for this can strengthen acid-base interpretation and lower the risk of missing a clinically meaningful high gap.
Albumin correction is especially valuable when assessing patients with severe illness, inflammation, liver disease, or poor nutrition. In those settings, an apparently normal anion gap may mask a true acid-base disorder. This is one reason the corrected value is often more informative than the unadjusted number alone.
Using an Anion Gap Calculator in Simple Steps
An anion gap calculator is straightforward, but precision matters. The tool is only as helpful as the lab values entered into it, so it is important to use the correct numbers listed by the laboratory.
- Find the serum sodium, serum chloride, and serum bicarbonate from the lab report. Type those numbers into the calculator input fields. Determine whether the calculator includes an albumin adjustment option. Examine the calculated anion gap value and compare it with the stated reference range. Interpret result interpretation in the context of symptoms, history, and other labs.
If the calculator provides a reference range, evaluate the result to that range rather than treating one universal cutoff. Different laboratories may use slightly different methods or reporting standards. That means a result that is borderline in one setting may be considered acceptable in another.
For best use, the calculator should be seen as a helpful interpretation tool, not a replacement for professional judgment. It can support pattern recognition, but it cannot diagnose the cause of an abnormal result by itself. A careful clinician will combine the anion gap with the patient’s condition, other blood chemistry markers, and any relevant symptoms.
In practice, a calculator can be a fast way to identify whether the data suggest an acid-base disorder, whether albumin correction is needed, and whether the pattern should prompt a more detailed diagnostic workup. That makes it a useful tool for clinical decision support and patient evaluation.
When to Consider A Clinical Review
An abnormal anion gap should be brought to a medical provider, especially when it appears alongside concerning symptoms. These may include difficulty breathing, confusion, vomiting, severe fatigue, dehydration, or signs of worsening illness. In the appropriate context, these symptoms can suggest metabolic acidosis or a separate serious condition.
Emergency care may be necessary if there are significant symptoms, altered mental status, breathing changes, or suspected toxin exposure. A high gap in the setting of illness can indicate a potentially serious NAGMA causes metabolic derangement that should not be ignored. If toxic alcohol ingestion is possible, prompt evaluation is particularly important.
Even a low or normal result may warrant further evaluation if the patient has persistent symptoms or other abnormal findings. The calculator is valuable for screening and interpretation, but it is not a substitute for medical advice. A provider can determine whether the result fits the larger clinical picture and whether additional testing is needed.
In short, the anion gap is one part of a broader lab interpretation process. It helps identify patterns, but the real value comes from connecting those patterns to the patient’s overall presentation.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used for analysis of laboratory values and medical decision-making support. It helps determine the https://anion-gap-widget015.bearsfanteamshop.com/how-the-anion-gap-aids-identify-acid-base-disorders anion gap from serum sodium, serum chloride, and serum bicarbonate, which can reveal clues about acid-base balance, electrolyte imbalance, and possible metabolic acidosis.
What is the normal anion gap range in adults?
The normal range can vary by laboratory and by the formula used, so the best answer is to check the specific reference range listed with the lab report. Some labs use a narrower or wider range depending on their methods and whether albumin correction is considered.
Why would the anion gap elevated in metabolic acidosis?
A high anion gap in metabolic acidosis typically indicates there are more unmeasured anions in the blood, such as lactate or ketones. This picture is often seen in high anion gap metabolic acidosis and can be due to lactic acidosis, ketoacidosis, renal failure, or toxic alcohol ingestion.
How do you calculate the anion gap for low albumin?
To adjust the anion gap for low albumin, clinicians use an albumin correction formula that modifies the measured value upward when hypoalbuminemia is present. Because albumin normally contributes negative charge through protein binding, a low level can make the raw result look falsely low. The corrected anion gap provides a more accurate picture for acid-base interpretation.
Is a low anion gap be a sign of a serious problem?
Yes, a low anion gap can occasionally be associated with a serious problem, although it is often due to lab variation or low albumin. It should be reviewed in context, especially if there are other abnormal lab results or symptoms. A medical provider can determine whether it reflects a benign finding or needs a diagnostic workup.