What’s the Anion Gap?
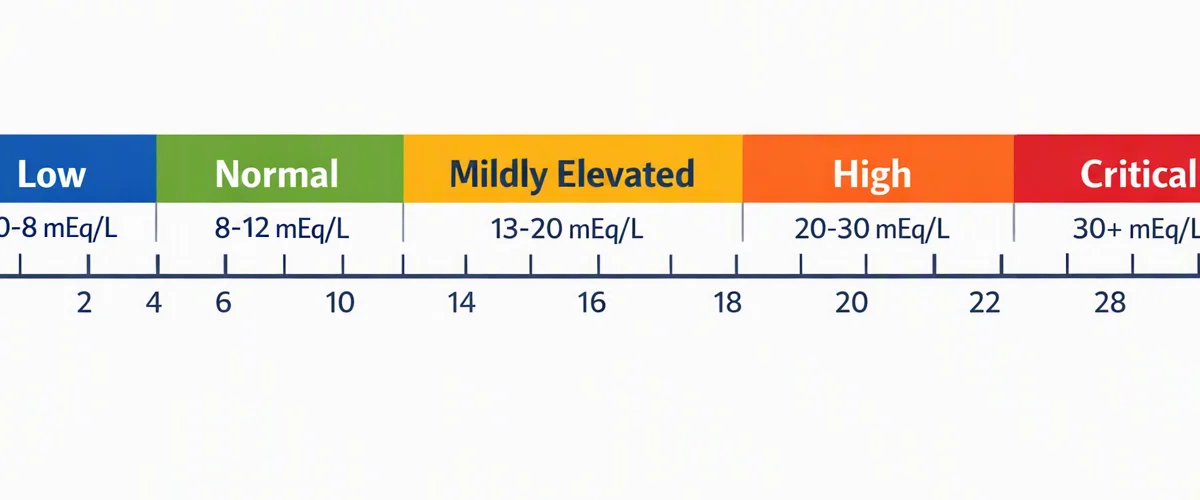
The anion gap is a derived value used osmolar gap anion gap comparison to help interpret electrolytes in a serum chemistry panel. It is not directly measured; instead of that, it is derived from key blood chemistry numbers such as sodium, chloride, and bicarbonate. Clinicians apply it as a diagnostic clue when evaluating acid-base balance, especially when a metabolic disorder may be present.
In plain language, the anion gap reflects the difference between the major positively charged particles and the major negatively charged particles reported on routine labs. Because sodium is the main measured cation and chloride and bicarbonate are the main measured anions, shifts in these values can affect the calculated result. That is why chloride is so important in clinical interpretation.
The anion gap is often used to identify whether there are unmeasured acids in the blood. A change in chloride can make the result look higher or lower even when the underlying cause is elsewhere. Understanding this relationship helps explain why a lab value may be an abnormal result without standing alone as a diagnosis.
In What Way Chloride Is Used In the Anion Gap Formula
The traditional anion gap formula appears as:
Anion gap = sodium - (chloride + bicarbonate)
That makes the function of chloride especially clear. When chloride rises while sodium and bicarbonate remain unchanged, the calculated anion gap falls. If chloride decreases, the calculated anion gap goes up. Put differently, chloride is one of the key factors of the number you observe on the screen when using an anion gap calculator.
Because bicarbonate is also part of the formula, a change in either chloride or bicarbonate can affect the final value. That is why, a single lab result should always be interpreted in the context of the full blood chemistry pattern, not in isolation. The result is a calculated value, not a direct measurement of a hidden toxin or acid.
For many people, the most useful way to think about the formula is that sodium tends to anchor the number, while chloride and serum bicarbonate push it up or down. When chloride increases, the gap narrows. When chloride decreases, the gap becomes larger. That simple relationship is central to acid-base balance.
Why Chloride Can Change When the Anion Gap Changes
This electrolyte doesn’t always change on its own. The body often adjusts chloride to maintain electrical neutrality and preserve acid-base balance. That means the pattern may reflect compensation rather than a primary problem with chloride itself.
Hyperchloremia means a elevated chloride level. It often occurs when bicarbonate falls, because chloride may rise to compensate for the loss of negative charge. This pattern is often seen in metabolic acidosis, especially when the body is losing bicarbonate through the gut or kidneys.
Hypochloremia means a decreased chloride level. This can occur when bicarbonate is relatively high, which is more consistent with metabolic alkalosis. In that setting, the body may hold onto bicarbonate or shed acid, and chloride often drops as part of the overall pattern.
These shifts are important because they help show why chloride is not just a background number. It often functions as a marker of the body’s response to a metabolic disorder. The chloride shift can be a useful clue for identifying whether the issue is more likely acid retention, base loss, volume depletion, or a combination of factors.
Understanding What a High Anion Gap Means for Chloride Values
A increased anion gap usually suggests that hidden acids are circulating in the blood. In most situations, chloride is not the primary cause of the elevated gap, but it can still help reveal the pattern. The key idea is that when the body accumulates acids, bicarbonate is often used up, and chloride may not rise enough to offset the change.
Common causes of a high anion gap include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, lactic acid rises during poor oxygen delivery or severe illness. In ketoacidosis, ketones accumulate when the body burns fat as a major fuel source. In renal failure, the kidneys cannot clear acids effectively, so the blood becomes more acidic.
These conditions can produce distinct lab values. For example, bicarbonate may be low, sodium may be relatively stable, and chloride may be within range or only mildly changed. The important point is that a high anion gap often indicates that the acid-base balance is being disrupted by acids other than chloride. This is why chloride is part of the pattern but not the sole explanation.
When reviewing a high anion gap, it helps to look at the whole blood chemistry profile. A clinician may compare sodium, chloride, bicarbonate, albumin, and kidney function together. That broader view can differentiate a simple electrolyte imbalance from a more serious systemic illness.
What a Reduced Anion Gap May Mean for Chloride Levels
A low anion gap is not as common, but it can be clinically meaningful. One frequent reason is hypoalbuminemia, because albumin is an major unmeasured negatively charged protein. When albumin falls, the calculated gap may also decrease, even if chloride is normal.
Another cause is lab error. Because the anion gap is a calculated value, any minor problem in the measured components can alter the final result. A specimen problem, contamination, or analytic variation can produce an unexpectedly low number that does not reflect the patient’s true physiology.
Paraproteinemia is another important cause. In some blood disorders, abnormal proteins change the charge balance in the serum, which can lower the calculated gap. This pattern can be a useful clue during clinical interpretation, especially when other lab values also look unusual.
Chloride may be normal, low, or sometimes relatively high in low-gap states depending on the cause. The main point is that a low anion gap does not automatically mean chloride is the problem. It may instead reflect protein levels, measurement issues, or other blood chemistry changes.
How to Use an Anion Gap Calculator Properly
An anion gap calculator is useful for a fast review, but it is most reliable when the input values come from the same serum chemistry panel. Mixing values from different draws or different time points can result in misleading conclusions. A careful user should confirm that sodium, chloride, and bicarbonate are in the same lab set.
It is also important to know the lab’s reference range, because the normal range can vary by method and analyzer. Some labs apply a slightly different formula or report a different range depending on whether potassium is included. That means one lab’s normal range may not correspond to another’s exactly.
If albumin is low, think about an albumin correction. Since albumin affects the charge balance, the corrected anion gap may more clearly show the true acid-base picture. This matters when looking for an occult metabolic acidosis or when the uncorrected value seems less significant than the clinical picture suggests.
Using the calculator well means viewing it as one part of lab interpretation. The result is a calculated value that should be reviewed alongside serum chloride, serum bicarbonate, albumin, and the overall clinical context. The calculator gives a starting point, not a final diagnosis.
Typical Reasons of Abnormal Chloride and Anion Gap Results
A number of everyday medical scenarios can alter both chloride and the anion gap. Fluid loss can compress blood elements and affect lab values, at times modifying chloride and sodium together. In relation to the overall state of volume loss, the numbers may look subtly or markedly different.
Nausea and vomiting often causes depletion of gastric acid and can lead to hypochloremia and metabolic alkalosis. In this pattern, bicarbonate may be relatively higher, chloride may be reduced, and the anion gap may be unchanged or only mildly changed. The lab pattern can be a helpful diagnostic clue for the source of the acid-base disturbance.
Frequent bowel movements often causes bicarbonate loss from the gastrointestinal tract. This can produce a nonanion-gap metabolic acidosis with hyperchloremia, because chloride rises as bicarbonate falls. In this typical pattern, the chloride increase helps explain why the anion gap does not rise much even though the patient is acidotic.
Saline treatment can also affect the pattern. Large amounts of normal saline may raise chloride and reduce bicarbonate, leading to hyperchloremic metabolic acidosis and a smaller anion gap. This is a classic example of how treatment itself can change blood chemistry and influence clinical interpretation.
These situations show why the anion gap and chloride must be reviewed together rather than separately. One lab may point toward volume loss, gastrointestinal loss, fluid administration, or an underlying metabolic disorder. The pattern matters as much as the number.
When to Seek a Clinician for Review
Any kind of acid-base disorder ought to be reviewed by a clinician, especially if there are symptoms or several lab abnormalities occur together. An isolated abnormal value may not be immediately concerning, but a pattern involving sodium, chloride, bicarbonate, and albumin can indicate a more complex problem.
A clinician may arrange or interpret an arterial blood gas when the situation is hard to assess. This test helps measure pH, carbon dioxide, and oxygen status, which can help determine whether the abnormal chemistry panel reflects true acidosis or alkalosis. It can also help distinguish compensation from primary disease.
People with known kidney disease should monitor these numbers, since kidney function strongly affects acid removal and electrolyte balance. Impaired kidney function can cause a rising high anion gap, especially when acid clearance declines. The same is true in advanced illness where the metabolic state is unstable.
It is wise to ask for interpretation when there is persistent electrolyte imbalance, symptoms such as confusion or weakness, or a result that does not fit the clinical picture. Lab values are most useful when interpreted as part of the whole story, including medications, hydration status, and recent illness.
FAQs About the Anion Gap and Chloride
How are chloride and anion gap related?
They are directly related through the anion gap formula. Because chloride is subtracted along with bicarbonate from sodium, a higher chloride level usually reduces the anion gap, while a lower chloride level can increase it. This relationship makes chloride a key part of acid-base balance and blood chemistry interpretation.
Does a high chloride level mean a low anion gap?
In many cases, yes, but not always by itself. A high chloride level, or hyperchloremia, tends to lower the calculated gap because chloride is one of the values in the formula. However, the final result also depends on sodium, bicarbonate, albumin, and whether there is a larger metabolic disorder affecting the blood chemistry.
Can the anion gap be normal when chloride is abnormal?
Yes. A typical anion gap can still occur even if chloride is abnormal, notably when bicarbonate changes in the reverse direction or when the body is responding for another problem. That is why lab interpretation should look at the entire pattern rather than focusing on a one chloride level or a one calculated value.
Why does low albumin affect the anion gap?
Low albumin lowers the anion gap because albumin is an key unmeasured negatively charged protein. When albumin falls, the calculated gap may drop even if the true acid-base state is different. That is why a corrected anion gap can be helpful when hypoalbuminemia is present.
Should I use an anion gap calculator with corrected albumin?
Yes, when albumin is low or when the clinical picture suggests the uncorrected result may be misleading. An albumin correction can give a more accurate estimate of the acid-base situation, notably when evaluating metabolic acidosis or other systemic illness. A calculator is most helpful when paired with the serum chemistry panel and professional clinical interpretation.